
More Hair Than Usual in the Shower or Brush
Persistent shedding may follow illness, stress, weight change or another trigger, but it can also reveal an underlying hair-loss condition.
Hair shedding, thinning and changes in density can look similar while representing very different conditions.
At Dermatology Circle, a hair loss dermatologist in NYC guides your care from diagnosis through medical treatment, selected procedures and long-term monitoring. Your plan is tailored to the type and stage of hair loss, scalp findings and individual goals.
Dr. Viktoryia Kazlouskaya is a board-certified dermatologist and dermatopathologist with a special focus on hair and scalp disorders, including pattern hair loss, excessive shedding, autoimmune alopecia and scarring conditions.

Hair loss often begins with subtle changes rather than a dramatic bald area. The pattern, scalp findings, timeline and changes in hair quality can provide important clinical clues.
Persistent shedding may follow illness, stress, weight change or another trigger, but it can also reveal an underlying hair-loss condition.
Gradual changes in density may become visible along the part or crown before hair loss seems obvious elsewhere.
Recession or reduced coverage can develop slowly. Standardized photographs can help reveal progression.
Progressive miniaturization can make individual hairs finer before a dramatic change in visible density develops.
Scalp symptoms may provide important clues when inflammation is contributing to the hair-loss process.
Similar symptoms can have different causes. Temporary shedding, pattern hair loss, alopecia areata and scarring alopecia can also overlap.
The pattern, scalp findings, timeline and follicular changes help distinguish conditions that can initially look alike but require different treatment strategies.
Gradual thinning, widening of the part, recession or reduced density associated with progressive follicular miniaturization.
Explore Pattern Hair LossPatchy or diffuse hair loss caused by an autoimmune process affecting the hair follicles.
Explore Alopecia AreataDiffuse shedding that may follow illness, surgery, rapid weight loss, childbirth or another physiologic trigger.
Explore Telogen EffluviumInflammatory disorders associated with permanent follicular damage, where earlier recognition may be particularly important.
Explore Scarring AlopeciaInflammatory scarring disorders that may affect the scalp, frontal hairline, eyebrows and other hair-bearing areas.
Explore LPP & FFATelogen effluvium can occur together with pattern hair loss, and inflammatory scalp disease may coexist with another form of alopecia. Identifying each component can change the treatment strategy.
Hair-loss patterns, contributing factors and treatment considerations can differ between women and men.
Women frequently notice widening of the central part, reduced ponytail volume or diffuse thinning. Hormonal history, reproductive plans, nutrition and overlapping shedding may influence evaluation and treatment.
Male pattern hair loss commonly affects the frontal hairline, temples and crown, while excessive shedding or inflammatory disease may occur at the same time.
What looks like thinning on the surface may represent very different changes at the follicular level.
Clinical examination and digital trichoscopy can help identify miniaturization, inflammation, changes in density and clues to scarring disease. Laboratory testing or scalp biopsy is added selectively when the clinical findings raise a specific question.
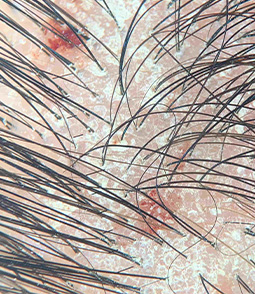
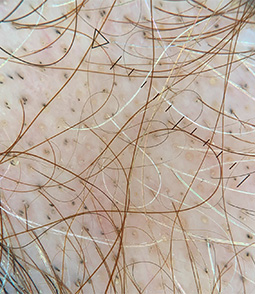

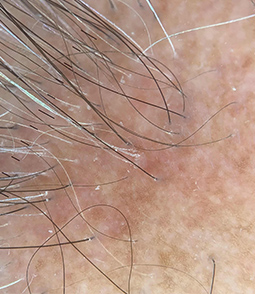
Trichoscopy adds evidence. The diagnosis comes from interpreting the entire clinical picture.
Hair-loss treatment should not begin with choosing a procedure. It should begin with determining what is happening to the follicles.
Depending on the diagnosis, treatment may focus on stimulating growth, slowing progressive miniaturization, controlling inflammation or addressing relevant contributing factors.
Topical or low-dose oral minoxidil may be considered in selected patients when supporting hair growth is part of the treatment strategy.
Oral Minoxidil for Hair LossFinasteride, dutasteride, spironolactone or other diagnosis-specific strategies may be considered according to sex, medical history, reproductive plans and clinical findings.
In inflammatory or scarring alopecia, controlling inflammation may be more important than simply stimulating growth because continued disease activity can permanently damage follicles.
Relevant scalp disease, nutritional deficiency, medication changes, hormonal factors or systemic illness are addressed when supported by the clinical picture.
A hair-growth medication should not replace a hair-loss diagnosis. Treatment is selected according to the process affecting the follicles.
Not every patient needs a procedure. Adjunctive treatments are considered when they add meaningful value to the diagnosis-specific medical plan.
PRP may provide additional support in selected nonscarring hair-loss conditions as part of a broader medical strategy.
Explore PRP 02 Targeted DeliveryLocal dutasteride delivery may be incorporated into an individualized off-label treatment strategy for selected patients with androgenetic alopecia.
Explore Mesotherapy 03 Laser-Assisted TreatmentLaser-assisted scalp treatment may complement selected nonsurgical hair-restoration protocols.
Explore KeraLase 04 At-Home SupportPhotobiomodulation may provide additional support for selected patients and does not replace diagnosis-specific medical treatment.
Learn About LLLTStandardized clinical photography can help document change more reliably than memory alone. Individual treatment plans, timelines and results vary.
View More Hair Loss Cases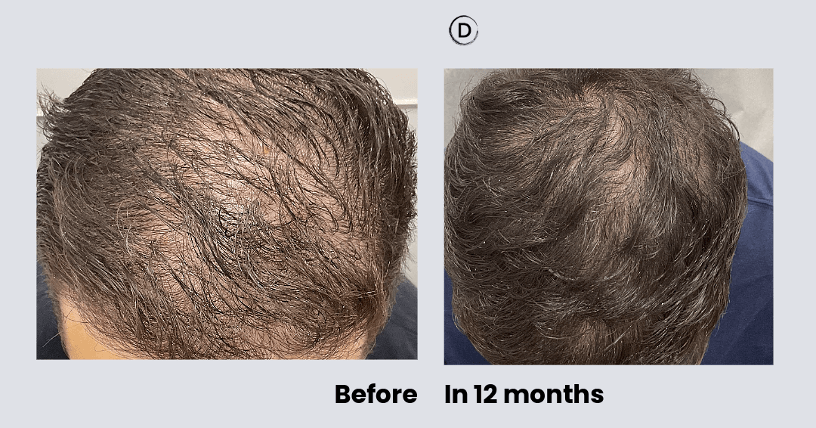
Change in density and coverage documented over twelve months.

Clinical improvement documented during longitudinal treatment.
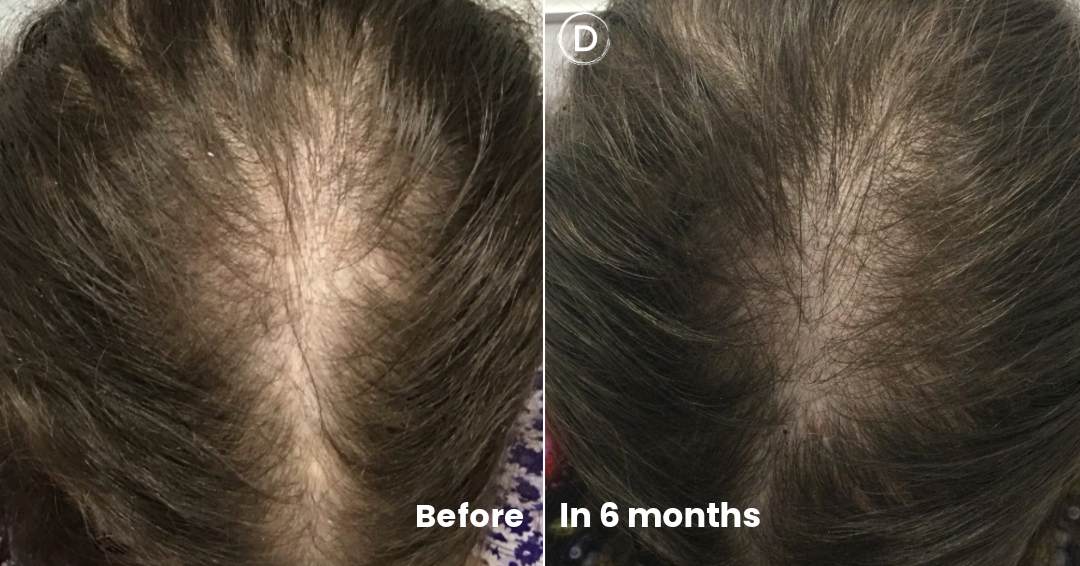
Improved central scalp coverage documented at follow-up.
What matters is not how many treatment options are available, but how carefully the clinical information is interpreted and how the plan is adjusted over time.
Treatment begins with identifying what process is actually affecting the hair.
Magnified imaging and standardized documentation create an objective baseline for follow-up.
Particularly useful when inflammatory or scarring hair-loss disorders are considered.
Medical treatment and procedures are selected according to diagnosis and individual priorities.
Follow-up helps determine whether the condition is stable, improving or continuing to change.

Board-Certified Dermatologist · Dermatopathologist
Hair loss is not one disease, and successful treatment depends on understanding which biological process is affecting the follicles.
Dr. Kazlouskaya evaluates hair loss from a medical dermatology perspective, with particular attention to clinical pattern, scalp findings, follicular miniaturization and signs of inflammation.
Her background in dermatopathology provides additional perspective when inflammatory, scarring or diagnostically complex hair-loss conditions are considered.
“With hair loss, my first goal is to understand which process is actually affecting the follicles.”
Dermatology Circle provides physician-led evaluation and treatment for hair thinning, excessive shedding, alopecia and scalp disorders in New York City.
Hair loss can look similar on the surface while representing very different conditions underneath.
A dermatologist is a medical doctor trained to diagnose conditions affecting the hair, scalp and skin. Medical evaluation is particularly important when inflammation, autoimmune disease, scarring or another medical condition may be involved.
The visit typically includes a detailed history and examination of the hair and scalp. Digital trichoscopy may be used when magnified evaluation can provide clinically useful information.
What to Expect During a Hair Loss ConsultationNo. There is no universal laboratory panel for every patient. Testing is selected according to the history, examination and suspected diagnosis.
A scalp biopsy may be considered when the diagnosis remains uncertain or when inflammatory or scarring alopecia is suspected.
Yes. Telogen effluvium can occur together with androgenetic alopecia, and inflammatory disease may coexist with another form of hair loss.
Not necessarily. Shedding refers to increased release of hairs, while progressive hair loss may involve miniaturization, reduced density or follicular damage.
No. Different hair-loss disorders have different mechanisms and treatment priorities. The appropriate plan depends on the diagnosis and individual clinical situation.
Hair changes slowly. Meaningful improvement commonly takes several months, and in some conditions stabilization is the first treatment goal.
Once a follicle has been permanently destroyed by scarring, regrowth from that follicle may not be possible. Treatment focuses on controlling disease activity and protecting follicles that remain viable.
Consider evaluation when shedding persists, density changes, the part or hairline looks different, or scalp symptoms develop. Earlier assessment is particularly reasonable for rapid or patchy loss, burning, redness or scaling.
You do not need to know which type of hair loss you have before scheduling. The evaluation is designed to determine what process may be affecting the follicles and what should happen next.